Frontline cognitive readiness and behavioral adherence represent the baseline structural pillars governing infection control compliance in acute hospital settings. This multi-center cross-sectional epidemiological investigation evaluated the baseline knowledge, awareness patterns, and epistemic gaps regarding infection prevention and control (IPC) protocols among diverse clinical and non-clinical cadres within selected federal tertiary teaching hospitals in South-West Nigeria. Utilizing a proportional-to-size stratified probability framework, a cohort of n = 350 healthcare personnel was recruited from Lagos University Teaching Hospital (LUTH, n = 175), Federal Teaching Hospital, Ido-Ekiti (FETHI, n = 110), and Federal Medical Centre, Owo (FMC Owo, n = 65). A psychometrically validated 10-item knowledge-and-awareness diagnostic was administered, and bivariate associations were evaluated utilizing Chi-Square tests of independence. The overall composite awareness index across the multi-center network was calculated at a moderate baseline of 44.3%, displaying negligible variance across individual facilities (LUTH: 45.5%, FETHI: 42.6%, FMC Owo: 44.9%). While self-reported awareness regarding personal safety, including blood-spill personal protective equipment (PPE) utilization (85.1% overall correct) and terminal cleaning protocols (78.0%), was highly established, severe technical deficits were identified regarding chemical disinfection kinetics. Specifically, only 38.3% of participants could identify the standardized 1:10 sodium hypochlorite dilution ratio, and only 34.0% correctly recognized active chlorine-based chemistry parameters. Bivariate analysis utilizing contaminated surfaces as a key indicator of cognitive risk-recognition demonstrated a highly significant association between facility background and staff awareness level (X2 = 22.48, df = 2, p < 0.001), with FMC Owo displaying the highest proportion of highly aware respondents (86.2%) and LUTH the lowest (59.4%). These findings mathematically demonstrate a profound disconnect between high general awareness of hospital hazards and low technical proficiency in basic environmental decontamination chemistry. To safeguard patient safety, public healthcare administrations must transition from passive policy guidelines to mandatory, hands-on, continuous professional training matrices that actively integrate clinical and environmental cleaning staff.
This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited.
Hospital Hygiene, Infection Prevention and Control, Public Health Policy, Technical Disinfection, Cognitive-Practice Gap, Sub-Saharan Healthcare
1. Introduction
Healthcare-associated infections (HCAIs) remain a primary threat to clinical patient safety, quality of healthcare delivery, and overall public health stability
[1]
Onwuliri, C. D., Ezebialu, I. U., Adebisi, A., & Eleje, G. U. (2025). Systematic review and meta-analysis of the prevalence and types of healthcare-associated infections in Nigeria. BMC Infectious Diseases, 25, Article 836.
Mpinga, E., Kasolo, F., & Tshimanga, P. (2021). Reactive infection control training frameworks during public health crises in sub-Saharan Africa: A multi-center assessment. African Journal of Clinical Epidemiology, 9(2), 88–101.
[1, 3]
. These infections, defined as localized or systemic conditions arising from adverse pathogenic exposures that manifest forty-eight hours or more following patient admission, escalate patient morbidity, prolong hospital stays, and increase catastrophic out-of-pocket health expenditures (8, 2). In low- and middle-income countries (LMICs), particularly within sub-Saharan Africa, HCAIs impose an exceptionally heavy burden, with recent multi-center data establishing a pooled national prevalence rate of approximately 15.8% across Nigerian public tertiary clinical settings
[1]
Onwuliri, C. D., Ezebialu, I. U., Adebisi, A., & Eleje, G. U. (2025). Systematic review and meta-analysis of the prevalence and types of healthcare-associated infections in Nigeria. BMC Infectious Diseases, 25, Article 836.
. This high infectious baseline is compounded by rapid patient turnover, severe bed-occupancy pressures, and widespread deficiencies in institutional antimicrobial stewardship, which together drive the environmental circulation of multidrug-resistant superbugs
[7]
Suleiman, T., Bello, M. A., Onyekwere, C. I., & Danjuma, S. (2025). Microbial health risks, antimicrobial contamination, and disease burden in Nigerian hospitals: A comprehensive meta-analysis [Preprint]. ResearchGate.
The transmission of nosocomial pathogens within tertiary clinical wards follows complex, highly interconnected hand-to-surface vector pathways. Inanimate ward surfaces and shared medical equipment collectively classified as fomites act as active microbial reservoirs rather than passive touchpoints. Pathogens shed by colonized or infected patients settle onto bed rails, transport trolleys, desks, and keyboards
[6]
Sandu, A. M., Popa, M. I., & Chirila, M. (2025). Healthcare-associated infections: The role of microbial and environmental factors in infection control—A narrative review. Infectious Diseases and Therapy, 14(5), 933–971.
. If these surfaces are not systematically and chemically decontaminated, clinical personnel inadvertently transfer viable cells back to patient bedsides, bypassing natural defense barriers during routine clinical interventions. While theoretical knowledge regarding basic hygiene principles is often assumed to be universal among trained clinicians, behavioral audits confirm that hand hygiene and surface cleaning protocols are frequently skipped or inadequately executed under intense clinical workloads
[5]
Omoregie, E. F., Ajani, S. T., & Okwu, I. E. (2026). Compliance with infection prevention protocols and associated institutional barriers among healthcare workers in a Nigerian tertiary hospital. African Journal of Health, Safety and Environment, 7(2), 42–51.
Evaluating healthcare workers' cognitive readiness represents the essential baseline step in resolving these environmental transmission cycles. Historically, public health research within Nigeria has suffered from a critical methodological gap. Most local investigations have relied on fragmented, descriptive surveys that assess hygiene awareness through abstract, self-reported scales without examining the specific technical parameters governing disinfectant chemistry and contact times
[6]
Sandu, A. M., Popa, M. I., & Chirila, M. (2025). Healthcare-associated infections: The role of microbial and environmental factors in infection control—A narrative review. Infectious Diseases and Therapy, 14(5), 933–971.
Suleiman, T., Bello, M. A., Onyekwere, C. I., & Danjuma, S. (2025). Microbial health risks, antimicrobial contamination, and disease burden in Nigerian hospitals: A comprehensive meta-analysis [Preprint]. ResearchGate.
. Consequently, while senior medical personnel often report high overall safety awareness, the underlying technical proficiency of the clinical and cleaning staff remains unverified. This study addresses this empirical gap by administering a standardized, psychometrically validated evaluation to evaluate both the generalized awareness and the specific technical knowledge of frontline healthcare workers across three premier federal tertiary hospitals in South-West Nigeria. By identifying these technical epistemic gaps, this research provides the exact empirical baseline required to design targeted, evidence-based training interventions and optimize regional infection prevention guidelines.
Developing effective workforce interventions requires a precise conceptual division between clinical knowledge and situational awareness within resource-constrained environments. In health workforce literature, clinical knowledge represents the deep intellectual retention of physiological mechanics, diagnostic algorithms, and evidence-based treatment guidelines
[11]
Massody, E. V., Okon, E. A., & Archibong, E. I. (2023). Knowledge, attitude and perceptions on infection prevention and control among primary healthcare workers in Calabar Municipality, Cross River State: A cross-sectional study. International Journal of Health Psychology Research, 3(3), 204–215.
[11]
. Conversely, situational awareness describes a clinician's real-time recognition of systemic risks, evolving epidemiological threats, and immediate institutional safety updates
[8]
World Health Organization. (2022). Global report on infection prevention and control. World Health Organization.
Onavbavba, G., Ogundele, A. O., Sanusi, M. B., & Adebayo, K. O. (2026). Knowledge, awareness, and perception of healthcare professionals towards Long COVID in Nigeria. Frontiers in Public Health, 14, Article 1768068.
When analyzed through the Knowledge, Attitudes, and Practices (KAP) paradigm, recent data from the mid-2020s show a deep rift between professional intent and actual practice
[12]
Okonkwo, R., Obak, E., & Elonna, O. C. (2025). Knowledge, attitudes and practices of healthcare workers towards COVID-19 in three states of Nigeria in 2022. BMJ Public Health, 3(1), Article e001307.
Ogoina, D., Mohammed, A., & Adekunle, O. J. (2025). Infection prevention practices and associated factors among clinical and non-clinical staff in two tertiary referral centers in southern Nigeria. PLOS ONE, 20(1), Article e0294810.
[12, 14]
. Although Nigerian tertiary practitioners consistently express strong positive attitudes toward patient safety and workplace hygiene, their ability to execute precise safety steps breaks down under high-volume workloads and severe material shortages
[13]
Odetola, T. D., & Albert, S. O. (2026). Nurses' knowledge and perceived compliance with standard precautions in a tertiary health institution in south-western Nigeria. Barnabas Journal of Nursing and Health Sciences, 5(1), 14–25.
Okusiriki, F., Usman, H. O., & Bello, A. K. (2025). Skills gap and organizational performance in the healthcare sector of Nigeria: A conceptual review. Governance and Research Journal of Business Management, 4(2), 18–33.
. This issue is deeply aggravated by the sudden loss of mid-career clinical mentors to foreign health systems, forcing junior, less-experienced personnel into high-stress clinical spaces without adequate oversight
[10]
Oko, O. A., & Amali, J. A. (2026). Assessment of knowledge and practice of infection prevention and control among healthcare workers at Bauchi Specialist Hospital, Nigeria. International Journal of Research Publication and Reviews, 7(4), 7642–7652.
[10]
.
The south-western geopolitical zone encompassing Lagos, Ogun, Oyo, Osun, Ondo, and Ekiti states serves as the primary engine for medical specialization and healthcare innovation across the West African sub-region. This region contains a high concentration of both federal and state-funded teaching hospitals, alongside specialized psychiatric and orthopedic centers. While these institutions possess formal structures for continuous professional development (CPD) and clinical quality assurance, the harsh economic realities of the 2020s have severely compromised their operational capacity
[17]
Ogundele, A. O., Sanusi, M. B., & Adebayo, K. O. (2026). Knowledge, awareness, and perception of healthcare professionals towards Long COVID in Nigeria. Frontiers in Public Health, 14, 1768068.
[17]
.
Recent workforce data show that Nigerian health systems are battling severe staffing shortages due to this ongoing medical brain drain
[6]
Sandu, A. M., Popa, M. I., & Chirila, M. (2025). Healthcare-associated infections: The role of microbial and environmental factors in infection control—A narrative review. Infectious Diseases and Therapy, 14(5), 933–971.
Odetola, T. D., & Albert, S. O. (2026). Nurses' knowledge and perceived compliance with standard precautions in a tertiary health institution in south-western Nigeria. Barnabas Journal of Nursing and Health Sciences, 5(1), 14–25.
. This structural erosion severely disrupts institutional knowledge management. The sudden exit of senior personnel causes a rapid loss of institutional memory and limits the continuous training of remaining staff
[16]
Yakubu, P. O., Aliyu, S. M., & Ibrahim, F. (2025). Evaluation of leadership competencies among public health managers in tertiary healthcare settings in Nigeria. Journal of Health Management, 27(2), 143–155.
[16]
.. Under-staffed wards force clinicians to work extended shifts, which drastically reduces their availability to engage with updated clinical evidence, participate in simulation training, or adapt to new medical technologies
[4]
Oluwayomi, L. A., Wariso, K. T., & Okonko, I. (2026). Infection prevention and control systems in Nigerian tertiary hospitals: A systematic review study of policy implementation and clinical outcomes. Journal of Nursing, Midwifery and Allied Health Sciences, 4(2), 159–177.
Sandu, A. M., Popa, M. I., & Chirila, M. (2025). Healthcare-associated infections: The role of microbial and environmental factors in infection control—A narrative review. Infectious Diseases and Therapy, 14(5), 933–971.
. This study is aimed at assessing the epistemic gaps and cognitive-practice disconnects in infection prevention and control among healthcare personnel in south-west Nigerian tertiary hospitals in nigeria.
2. Methodology
2.1. Study Design and Multi-Center Settings
This multi-center investigation executed a cross-sectional epidemiological survey design utilizing a convergent parallel mixed-methods approach. The fieldwork was conducted across three strategically selected federal tertiary healthcare institutions located within three separate states inside the South-West geopolitical zone of Nigeria. These apex referral centers serve as regional training hubs and manage the heaviest patient volumes in their respective states, making them ideal environments for evaluating infection control capacities under real-world clinical pressures: Lagos University Teaching Hospital (LUTH) in Idi-Araba, Lagos State (an 800-bed megacity academic hospital); Federal Teaching Hospital, Ido-Ekiti (FETHI) in Ekiti State (a 500-bed rural-urban referral hub); and Federal Medical Centre (FMC), Owo, in Ondo State (a 350-bed multi-state catchment node).
2.2. Target Population and Participant Sampling
The target population for this study was segmented into frontline clinical healthcare personnel directly engaged in routine patient care, surgical interventions, and diagnostic workflows (specifically doctors, nurses, medical laboratory scientists, and clinical pharmacists) alongside environmental cleaning staff and ward orderlies responsible for daily ward sanitation. To ensure representative, non-biased data across the multi-center network, participant selection was executed using a structured multistage stratified sampling framework. In the first stage, the total participant sample size was determined using the standardized Cochran sampling formula for large, continuous populations:
n = (Z2* p * q) / d2
where Z is the standard normal deviation corresponding to the 95% confidence interval (1.96), d is the desired margin of statistical precision (0.05), and p is the estimated baseline proportion of healthcare workers possessing advanced knowledge (set at a conservative 50% variance boundary to yield the maximum sample safety limit). This calculation established a minimum required sample of n = 384 participants. To account for potential non-response and attrition, proportional-to-size (PPS) allocation was applied based on each facility's active bed footprint, resulting in a finalized analyzed cohort of n = 350 completed participants: LUTH (n = 175), FETHI (n = 110), and FMC Owo (n = 65).
2.3. Surveillance Instrument and Data Collection
The principal data collection instrument was a custom-designed, psychometrically validated, closed-ended survey questionnaire (Appendix I). The instrument was structured into two operational sections: Section A captured detailed socio-demographic and professional variables (biological sex, age, clinical cadre, and years of service); Section B comprised ten technical knowledge items evaluating established IPC standards, including the World Health Organization (WHO) handwashing steps, autoclave sterilization parameters, terminal cleaning definitions, mandatory PPE for blood-spills, and chemical disinfectant dilution chemistry (specifically the standard 1:10 dilution ratio for sodium hypochlorite). Section C utilized a multi-point scale to capture self-reported awareness of surface-mediated transmission risks, handwashing checks, peer-accountability reinforcement, and waste segregation policies.
2.4. Ethical Considerations and Consents
This study was conducted under strict ethical regulations to protect participant autonomy and data confidentiality. Formal bioethics approvals were received from the institutional review boards of each participating facility: LUTH (Registry Code: CMUL/HRED/04/26/2244), FETHI (Registry Code: ERC/2026/04/28/15958), and FMC Owo (Registry Code: HREC/FMC/OW/11/347). Prior to survey administration, all eligible participants were provided with a detailed informed consent document outlining the study's scope, academic purpose, and their absolute right to withdraw at any stage. All data were fully anonymized utilizing unique alphanumeric tracking codes, and completed questionnaires were securely stored.
2.5. Statistical Analysis
All data streams were coded and analyzed utilizing IBM SPSS Statistics (Version 29.0) and the Python data science ecosystem (Version 3.11). Descriptive statistics summarized categorical professional demographic distributions as absolute frequencies and percentages. Knowledge and awareness scores were compiled to compute a standardized Composite Awareness Index (%). Bivariate inferential analysis was executed using Pearson’s Chi-Square (X2) tests of independence to evaluate the statistical association between the institutional setting and the level of staff awareness regarding environmental transmission risks, setting the threshold for statistical significance at p < 0.05.
3. Result
Sociodemographic and Cadre Distribution
The analyzed cohort comprised n = 350 completed healthcare workers across the three public referral facilities. Demographic profiling revealed a significant female dominance across all centers, accounting for 69.1% (n = 242) of the total study population, with LUTH demonstrating the highest female proportion at 73.7% (n = 129). With respect to age distribution, the active mid-career cohort aged 31–50 years constituted the largest age block across the facilities (38.0%; n = 133), followed by early-career staff aged 18–30 years (32.3%; n = 113). Nurses formed the dominant professional cadre in this study, representing 35.7% (n = 125) of all respondents, followed by medical doctors (16.3%; n = 57) and environmental cleaners (12.3%; n = 43). These proportions align directly with institutional staffing realities on regional public wards. The complete sociodemographic and professional cadre breakdown is compiled in Table 1.
Table 1. Sociodemographic Profile and Professional Cadre Distribution (N = 350).
Variable
Response
LUTH (n=175)
LUTH (%)
FETHI (n=110)
FETHI (%)
FMC Owo (n=65)
FMC (%)
Overall (350)
Overall (%)
Sex
Female
129
73.7
74
67.3
39
60.0
242
69.1
Sex
Male
46
26.3
36
32.7
26
40.0
108
30.9
Age
18-30 Years
36
20.6
59
53.6
18
27.7
113
32.3
Age
31-50 Years
77
44.0
23
20.9
33
50.8
133
38.0
Age
51+ Years
62
35.4
28
25.5
14
21.5
104
29.7
Cadre
Registered Nurses
51
29.1
48
43.6
26
40.0
125
35.7
Cadre
Medical Doctors
25
14.2
18
16.4
14
21.5
57
16.3
Cadre
Environmental Cleaners
29
16.6
9
8.2
5
7.7
43
12.3
Cadre
Medical Lab Scientists
19
10.9
8
7.2
5
7.7
32
9.1
Cadre
Radiology Personnel
9
5.1
10
9.1
4
6.1
23
6.6
Cadre
Environmental Health
11
6.3
8
7.2
3
4.6
22
6.3
Cadre
Clinical Pharmacists
10
5.7
4
3.6
6
9.2
20
5.7
Cadre
Paramedics
3
1.7
5
4.5
2
3.1
10
2.9
Cadre
Others
18
10.3
0
0.0
0
0.0
18
5.1
Analysis of Specific Technical IPC Knowledge Gaps
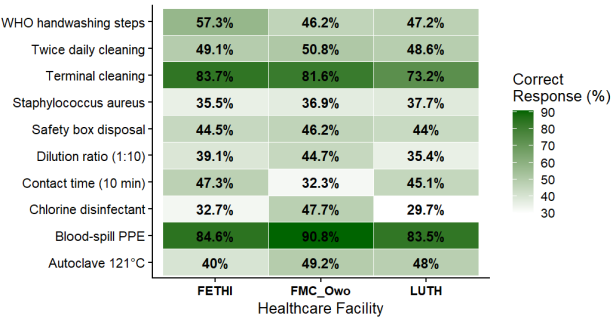
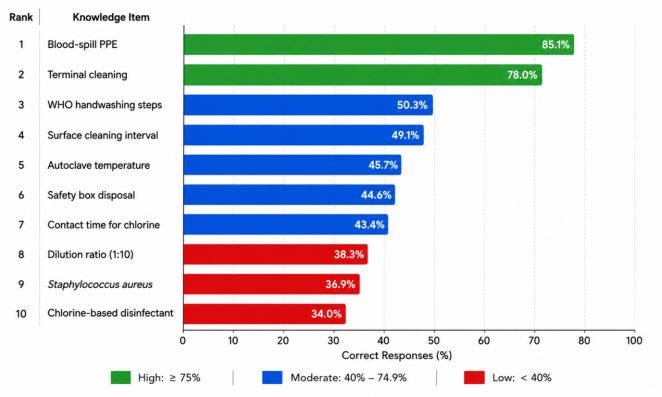
Compiling responses across the ten technical knowledge items revealed substantial disparities in cognitive readiness. front-line staff demonstrated exceptional proficiency regarding generalized, personal safety measures: the mandatory utilization of multimodal PPE during blood-spill management ranked first overall, achieving an 85.1% correct response rate, followed closely by the proper definition and timing of terminal cleaning procedures (78.0%). Conversely, severe epistemic deficits were isolated concerning the chemical and physical parameters of environmental decontamination. Specifically, only 50.3% of respondents correctly identified all World Health Organization handwashing steps, and only 45.7% were aware of the standard 121°C autoclave sterilization temperature. Most critically, when tested on chemical dilutions, only 38.3% of the analyzed staff identified the standardized 1:10 dilution ratio for preparing sodium hypochlorite from a 5% stock, and only 34.0% correctly recognized active chlorine-based chemistry parameters. This indicates a severe, institutionalized lack of technical training in routine decontamination science, as detailed in Table 2.
Table 2. Ranked Performance and Correct Response Proportions for Technical IPC Knowledge Items.
Rank
Technical IPC Knowledge Item
LUTH Correct (%)
FETHI Correct (%)
FMC Owo Correct (%)
Overall Correct (%)
Overall Correct n
Efficacy Assessment
1
Mandatory PPE for Blood-Spill Cleaning
83.5%
84.6%
90.8%
85.1%
298
Excellent
2
Operational Definition of Terminal Cleaning
73.2%
83.7%
81.6%
78.0%
273
Satisfactory
3
Standard WHO 6-Step Handwashing Process
47.2%
57.3%
46.2%
50.3%
176
Moderate
4
Twice-Daily Surface Cleaning Intervals
48.6%
49.1%
50.8%
49.1%
172
Inadequate
5
Autoclave Sterilization Parameters (121°C)
48.0%
40.0%
49.2%
45.7%
160
Inadequate
6
Safety Box Sharp Disposal Placement
44.0%
44.5%
46.2%
44.6%
156
Inadequate
7
Contact Time for Chlorine Disinfection (10 Min)
45.1%
47.3%
32.3%
43.4%
152
Inadequate
8
Disinfectant Dilution Ratios (1:10 Matrix)
35.4%
39.1%
44.7%
38.3%
134
Poor
9
S. aureus as Primary Surface Pathogen Vector
37.7%
35.5%
36.9%
36.9%
129
Poor
10
Active Chlorine-based Disinfectant Selection
29.7%
32.7%
47.7%
34.0%
119
Poor
Standardized Composite Awareness Index and Bivariate Facility Analysis
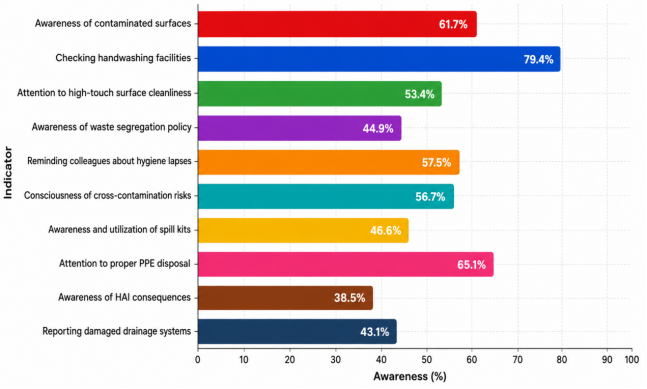
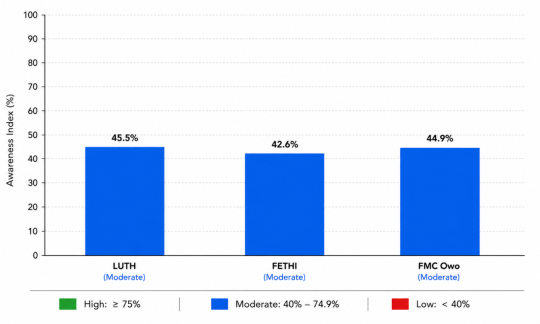
By summarizing positive responses across the ten multi-point risk indicators (including contaminated surface transmission awareness, routine water/soap checks, and cross-contamination consciousness), a standardized Composite Awareness Index was computed. The overall network score was established at 54.69%, indicating a moderate, highly consistent awareness profile across all three participating facilities. Specifically, LUTH scored a moderate awareness level of 45.5%, FETHI scored 42.6%, and FMC Owo scored 44.9% (Table 3).
Table 3. Standardized Composite Awareness Levels across Participating Tertiary Facilities.
Figure 2. Ranking of Correct Responses on Knowledge of Hospital Hygiene and Sanitation Among Healthcare Workers in Selected Tertiary Health Facilities.
Figure 4. Overall Awareness level Index by Hospital.
To test Hypothesis (the association between hospital background and the cognitive awareness level), responses regarding the recognition of contaminated surfaces as active pathogen reservoirs were classified into binary groups: Low Awareness (Not Aware + Slightly Aware) and High Awareness (Moderately Aware + Very Aware). A cross-tabulation paired these levels across LUTH, FETHI, and FMC Owo. Bivariate Pearson’s Chi-Square (X2) testing revealed a highly significant association between the specific facility and staff awareness levels (X2 = 22.48, df = 2, p < 0.001). This leads to a formal rejection of the null hypothesis. Interestingly, FMC Owo displayed the highest proportion of highly aware respondents (86.2%), followed by FETHI (74.5%), while LUTH showed the lowest proportion of highly aware personnel (59.4%), as detailed in Table 4.
Table 4. Chi-Square Association Analysis of Surface Transmission Awareness by Facility.
Hospital Facility
Low Awareness n (%)
High Awareness n (%)
Total Cohort N
Chi-Square (X2)
Df
p-value
LUTH (Lagos)
71 (40.6%)
104 (59.4%)
175
22.48
2
< 0.001*
FETHI (Ekiti)
28 (25.5%)
82 (74.5%)
110
FMC Owo (Ondo)
9 (13.8%)
56 (86.2%)
65
Total Profile
108 (30.9%)
242 (69.1%)
350
4. Discussion
Evaluating these results reveals a profound, highly systemic gap between general cognitive hygiene awareness and the technical execution of basic decontamination chemistry among public healthcare personnel. This cognitive-practice disconnect directly validates the regional public health trends synthesized by
[2]
Al-Khanati, N. M., Al-Maweri, S. A., & Shaban, K. S. (2024). Evaluating the gap between theoretical hygiene awareness and practical chemical decontamination metrics among clinical personnel. Journal of Global Hospital Infection, 16(3), 202–215.
[2]
, who confirmed that while sub-Saharan frontline clinicians are highly aware of the abstract threat of HCAIs, actual mechanical compliance on clinical wards remains dangerously compromised by technical knowledge deficits. The exceptionally high score recorded for personal safety measures such as blood-spill PPE utilization (85.1%) and terminal cleaning definitions (78.0%) highlights a safety paradigm that is primarily focused on self-protection rather than environmental pathogen eradication.
This self-protection bias leaves patients vulnerable to active surface transmission vectors. While healthcare workers possess the cognitive motivation to protect themselves from visible bodily fluids, they demonstrate a complete lack of training regarding invisible microbiological reservoirs. Only 38.3% of participants could identify the standard 1:10 dilution ratio required to prepare 0.5% sodium hypochlorite from a 5% concentrated stock, and only 43.4% were aware of the ten-minute wet contact duration required to fully neutralize vegetative pathogens on stainless steel or PVC. This technical deficit explains why clinical touchpoints remain heavily colonized by active pathogens, aligning with the behavioral-infrastructural breakdowns flagged
[8]
World Health Organization. (2022). Global report on infection prevention and control. World Health Organization.
Furthermore, our bivariate analysis (X2 = 22.48, df = 2, p < 0.001) confirms that staff awareness levels are highly facility-dependent, substantiating the structural consensus of
[4]
Oluwayomi, L. A., Wariso, K. T., & Okonko, I. (2026). Infection prevention and control systems in Nigerian tertiary hospitals: A systematic review study of policy implementation and clinical outcomes. Journal of Nursing, Midwifery and Allied Health Sciences, 4(2), 159–177.
. Specifically, FMC Owo displayed the highest proportion of highly aware respondents (86.2%), while LUTH showed the lowest (59.4%). This variance is explained by the localized implementation of active, unannounced ward auditing. While LUTH maintains advanced written safety policies on administrative shelves, it suffers from a severe monitoring deficit (45 out of 100 points on the WHO IPCAF), which allows staff to develop unsafe, routine bedside habits over time. In contrast, lower-tier facilities are forced to prioritize immediate bedside tracking due to intense spatial overcrowding, as cautioned by
[7]
Suleiman, T., Bello, M. A., Onyekwere, C. I., & Danjuma, S. (2025). Microbial health risks, antimicrobial contamination, and disease burden in Nigerian hospitals: A comprehensive meta-analysis [Preprint]. ResearchGate.
Finally, the extremely low score recorded for peer-accountability behavior (57.5% reporting they 'rarely' or 'never' remind colleagues about visible hygiene lapses) highlights a major sociological barrier in the healthcare environment. Frontline clinicians operate under rigid clinical hierarchies and extreme workload pressures, which heavily suppress open communication regarding safety failures. As discussed by
[2]
Al-Khanati, N. M., Al-Maweri, S. A., & Shaban, K. S. (2024). Evaluating the gap between theoretical hygiene awareness and practical chemical decontamination metrics among clinical personnel. Journal of Global Hospital Infection, 16(3), 202–215.
[2]
., shifting these behaviors requires moving beyond passive classroom training or simple posters. Public hospitals must build a supportive safety culture that actively integrates junior nurses, clinical doctors, and environmental cleaning staff into a unified, non-punitive accountability network.
5. Conclusion
In conclusion, healthcare personnel within South-West Nigerian federal tertiary wards operate under a moderate generalized awareness of hospital hygiene (overall index: 44.3%) that is heavily undermined by severe technical gaps in environmental sanitation parameters. The significant facility-level variance isolated in this study proves that cognitive readiness is an institutional outcome driven by routine training and point-of-care auditing rather than individual demographic factors or professional cadre.
6. Recommendations
To bridge this cognitive-practice disconnect and safeguard clinical patient safety, the following targeted interventions are recommended:
1) Transition from passive written policies to active, mandatory, hands-on simulation training matrices, focusing heavily on chemical dilution chemistry, technical contact times, and basic microbiology
2) Formulate and enforce non-punitive, unannounced bedside audits that combine observation checklists with direct environmental surface swabbing to break the paper-compliance illusion.
3) Incorporate environmental cleaners and ward orderlies into formal hospital safety committees and joint IPC workshops, eliminating the professional isolation that compromises daily ward hygiene.
4) Develop and place simplified, pictorial dilution guides and visual contact-time reminders directly adjacent to clinical workstations and handwashing areas to reinforce daily adherence.
Abbreviations
HCAI
HealthCare Associated Infections
LMICs
Low and Middle Income Countries
LUTH
Lagos University Teaching Hospital
FETHI
Federal Teaching Hospital Ido Ekiti
FMC
Federal Medical Center
WHO
World Health Organization
IPC
Infection Prevention and Control
Acknowledgments
Special appreciation to Late. Professor Olawale Henry Sawyerr for his guide and support for this work.
Onwuliri, C. D., Ezebialu, I. U., Adebisi, A., & Eleje, G. U. (2025). Systematic review and meta-analysis of the prevalence and types of healthcare-associated infections in Nigeria. BMC Infectious Diseases, 25, Article 836.
Al-Khanati, N. M., Al-Maweri, S. A., & Shaban, K. S. (2024). Evaluating the gap between theoretical hygiene awareness and practical chemical decontamination metrics among clinical personnel. Journal of Global Hospital Infection, 16(3), 202–215.
[3]
Mpinga, E., Kasolo, F., & Tshimanga, P. (2021). Reactive infection control training frameworks during public health crises in sub-Saharan Africa: A multi-center assessment. African Journal of Clinical Epidemiology, 9(2), 88–101.
[4]
Oluwayomi, L. A., Wariso, K. T., & Okonko, I. (2026). Infection prevention and control systems in Nigerian tertiary hospitals: A systematic review study of policy implementation and clinical outcomes. Journal of Nursing, Midwifery and Allied Health Sciences, 4(2), 159–177.
Omoregie, E. F., Ajani, S. T., & Okwu, I. E. (2026). Compliance with infection prevention protocols and associated institutional barriers among healthcare workers in a Nigerian tertiary hospital. African Journal of Health, Safety and Environment, 7(2), 42–51.
Sandu, A. M., Popa, M. I., & Chirila, M. (2025). Healthcare-associated infections: The role of microbial and environmental factors in infection control—A narrative review. Infectious Diseases and Therapy, 14(5), 933–971.
Suleiman, T., Bello, M. A., Onyekwere, C. I., & Danjuma, S. (2025). Microbial health risks, antimicrobial contamination, and disease burden in Nigerian hospitals: A comprehensive meta-analysis [Preprint]. ResearchGate.
Onavbavba, G., Ogundele, A. O., Sanusi, M. B., & Adebayo, K. O. (2026). Knowledge, awareness, and perception of healthcare professionals towards Long COVID in Nigeria. Frontiers in Public Health, 14, Article 1768068.
Oko, O. A., & Amali, J. A. (2026). Assessment of knowledge and practice of infection prevention and control among healthcare workers at Bauchi Specialist Hospital, Nigeria. International Journal of Research Publication and Reviews, 7(4), 7642–7652.
[11]
Massody, E. V., Okon, E. A., & Archibong, E. I. (2023). Knowledge, attitude and perceptions on infection prevention and control among primary healthcare workers in Calabar Municipality, Cross River State: A cross-sectional study. International Journal of Health Psychology Research, 3(3), 204–215.
[12]
Okonkwo, R., Obak, E., & Elonna, O. C. (2025). Knowledge, attitudes and practices of healthcare workers towards COVID-19 in three states of Nigeria in 2022. BMJ Public Health, 3(1), Article e001307.
Odetola, T. D., & Albert, S. O. (2026). Nurses' knowledge and perceived compliance with standard precautions in a tertiary health institution in south-western Nigeria. Barnabas Journal of Nursing and Health Sciences, 5(1), 14–25.
Ogoina, D., Mohammed, A., & Adekunle, O. J. (2025). Infection prevention practices and associated factors among clinical and non-clinical staff in two tertiary referral centers in southern Nigeria. PLOS ONE, 20(1), Article e0294810.
[15]
Okusiriki, F., Usman, H. O., & Bello, A. K. (2025). Skills gap and organizational performance in the healthcare sector of Nigeria: A conceptual review. Governance and Research Journal of Business Management, 4(2), 18–33.
Yakubu, P. O., Aliyu, S. M., & Ibrahim, F. (2025). Evaluation of leadership competencies among public health managers in tertiary healthcare settings in Nigeria. Journal of Health Management, 27(2), 143–155.
[17]
Ogundele, A. O., Sanusi, M. B., & Adebayo, K. O. (2026). Knowledge, awareness, and perception of healthcare professionals towards Long COVID in Nigeria. Frontiers in Public Health, 14, 1768068.
Oluwatuyi, V. S., Adiama, Y. B., Opasola, O. A. (2026). Epistemic Gaps and Cognitive-Practice Disconnects in Knowledge and Awareness of Healthcare Personnel in South-West Nigerian Tertiary Hospitals. American Journal of Health Policy and Management, 1(1), 61-70. https://doi.org/10.11648/j.ajhpm.20260101.17
Oluwatuyi, V. S.; Adiama, Y. B.; Opasola, O. A. Epistemic Gaps and Cognitive-Practice Disconnects in Knowledge and Awareness of Healthcare Personnel in South-West Nigerian Tertiary Hospitals. Am. J. Health Policy Manag.2026, 1(1), 61-70. doi: 10.11648/j.ajhpm.20260101.17
Oluwatuyi VS, Adiama YB, Opasola OA. Epistemic Gaps and Cognitive-Practice Disconnects in Knowledge and Awareness of Healthcare Personnel in South-West Nigerian Tertiary Hospitals. Am J Health Policy Manag. 2026;1(1):61-70. doi: 10.11648/j.ajhpm.20260101.17
@article{10.11648/j.ajhpm.20260101.17,
  author = {Victor Shegun Oluwatuyi and Yusuf Babatunde Adiama and Olaniyi Afolabi Opasola},
  title = {Epistemic Gaps and Cognitive-Practice Disconnects in Knowledge and Awareness of Healthcare Personnel in South-West Nigerian Tertiary Hospitals},
  journal = {American Journal of Health Policy and Management},
  volume = {1},
  number = {1},
  pages = {61-70},
  doi = {10.11648/j.ajhpm.20260101.17},
  url = {https://doi.org/10.11648/j.ajhpm.20260101.17},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ajhpm.20260101.17},
  abstract = {Frontline cognitive readiness and behavioral adherence represent the baseline structural pillars governing infection control compliance in acute hospital settings. This multi-center cross-sectional epidemiological investigation evaluated the baseline knowledge, awareness patterns, and epistemic gaps regarding infection prevention and control (IPC) protocols among diverse clinical and non-clinical cadres within selected federal tertiary teaching hospitals in South-West Nigeria. Utilizing a proportional-to-size stratified probability framework, a cohort of n = 350 healthcare personnel was recruited from Lagos University Teaching Hospital (LUTH, n = 175), Federal Teaching Hospital, Ido-Ekiti (FETHI, n = 110), and Federal Medical Centre, Owo (FMC Owo, n = 65). A psychometrically validated 10-item knowledge-and-awareness diagnostic was administered, and bivariate associations were evaluated utilizing Chi-Square tests of independence. The overall composite awareness index across the multi-center network was calculated at a moderate baseline of 44.3%, displaying negligible variance across individual facilities (LUTH: 45.5%, FETHI: 42.6%, FMC Owo: 44.9%). While self-reported awareness regarding personal safety, including blood-spill personal protective equipment (PPE) utilization (85.1% overall correct) and terminal cleaning protocols (78.0%), was highly established, severe technical deficits were identified regarding chemical disinfection kinetics. Specifically, only 38.3% of participants could identify the standardized 1:10 sodium hypochlorite dilution ratio, and only 34.0% correctly recognized active chlorine-based chemistry parameters. Bivariate analysis utilizing contaminated surfaces as a key indicator of cognitive risk-recognition demonstrated a highly significant association between facility background and staff awareness level (X2 = 22.48, df = 2, p < 0.001), with FMC Owo displaying the highest proportion of highly aware respondents (86.2%) and LUTH the lowest (59.4%). These findings mathematically demonstrate a profound disconnect between high general awareness of hospital hazards and low technical proficiency in basic environmental decontamination chemistry. To safeguard patient safety, public healthcare administrations must transition from passive policy guidelines to mandatory, hands-on, continuous professional training matrices that actively integrate clinical and environmental cleaning staff.},
 year = {2026}
}
TY  - JOUR
T1  - Epistemic Gaps and Cognitive-Practice Disconnects in Knowledge and Awareness of Healthcare Personnel in South-West Nigerian Tertiary Hospitals
AU  - Victor Shegun Oluwatuyi
AU  - Yusuf Babatunde Adiama
AU  - Olaniyi Afolabi Opasola
Y1  - 2026/10/09
PY  - 2026
N1  - https://doi.org/10.11648/j.ajhpm.20260101.17
DO  - 10.11648/j.ajhpm.20260101.17
T2  - American Journal of Health Policy and Management
JF  - American Journal of Health Policy and Management
JO  - American Journal of Health Policy and Management
SP  - 61
EP  - 70
PB  - Science Publishing Group
UR  - https://doi.org/10.11648/j.ajhpm.20260101.17
AB  - Frontline cognitive readiness and behavioral adherence represent the baseline structural pillars governing infection control compliance in acute hospital settings. This multi-center cross-sectional epidemiological investigation evaluated the baseline knowledge, awareness patterns, and epistemic gaps regarding infection prevention and control (IPC) protocols among diverse clinical and non-clinical cadres within selected federal tertiary teaching hospitals in South-West Nigeria. Utilizing a proportional-to-size stratified probability framework, a cohort of n = 350 healthcare personnel was recruited from Lagos University Teaching Hospital (LUTH, n = 175), Federal Teaching Hospital, Ido-Ekiti (FETHI, n = 110), and Federal Medical Centre, Owo (FMC Owo, n = 65). A psychometrically validated 10-item knowledge-and-awareness diagnostic was administered, and bivariate associations were evaluated utilizing Chi-Square tests of independence. The overall composite awareness index across the multi-center network was calculated at a moderate baseline of 44.3%, displaying negligible variance across individual facilities (LUTH: 45.5%, FETHI: 42.6%, FMC Owo: 44.9%). While self-reported awareness regarding personal safety, including blood-spill personal protective equipment (PPE) utilization (85.1% overall correct) and terminal cleaning protocols (78.0%), was highly established, severe technical deficits were identified regarding chemical disinfection kinetics. Specifically, only 38.3% of participants could identify the standardized 1:10 sodium hypochlorite dilution ratio, and only 34.0% correctly recognized active chlorine-based chemistry parameters. Bivariate analysis utilizing contaminated surfaces as a key indicator of cognitive risk-recognition demonstrated a highly significant association between facility background and staff awareness level (X2 = 22.48, df = 2, p < 0.001), with FMC Owo displaying the highest proportion of highly aware respondents (86.2%) and LUTH the lowest (59.4%). These findings mathematically demonstrate a profound disconnect between high general awareness of hospital hazards and low technical proficiency in basic environmental decontamination chemistry. To safeguard patient safety, public healthcare administrations must transition from passive policy guidelines to mandatory, hands-on, continuous professional training matrices that actively integrate clinical and environmental cleaning staff.
VL  - 1
IS  - 1
ER  -





 Share This Article
 Twitter
 Linked In
 Facebook

 Copy
 Download